Meet Julie—mother, wife, and person living with FCS. Join her as she shares her long road to diagnosis, discussing how identifying her condition has not only shaped her into the person she is today, but has also helped her manage the burden of her very high triglycerides.

Burden of extremely high triglycerides
The standard of care, including traditional triglyceride-lowering therapies and restrictive dieting or meal planning, may not be enough for people with Familial Chylomicronemia Syndrome (FCS). Expert guidelines support lowering triglycerides below 500 mg/dL to reduce the risk of acute pancreatitis.
Traditional treatment options are limited
Medicines traditionally used to lower triglycerides, such as statins, fibrates, and omega-3 fatty acids, may not suffice for people with extremely high triglycerides, including people with Familial Chylomicronemia Syndrome (FCS).
Statins
Statins may be useful in protecting against atherosclerotic cardiovascular disease (ASCVD); however, they are not clinically useful for people with FCS and do not lower acute pancreatitis risk.
Fibrates
Fibrates induce triglyceride clearance through various pathways, including by modestly increasing LPL and suppressing the transcription of apolipoprotein C3 (APOC3); however, the overall clinical benefit of fibrates in people with FCS is minimal.
Eicosapentaenoic Acid (EPA)
EPA, an omega-3 fatty acid, has been shown to moderately reduce triglyceride levels caused by other diseases but are not effective for people with FCS.
Traditional triglyceride-lowering therapies that are used to manage triglycerides have limited efficacy for people with FCS or with diseases with a similar presentation. Most traditional triglyceride-lowering therapies activate lipoprotein lipase (LPL) activity, which is missing or nonfunctional in people with FCS.
Restrictive diets can negatively impact quality of life
Some people use intensive dieting to manage high triglycerides; however, this strategy that avoids ingesting fats to maintain lower overall fasting triglycerides is very burdensome.
People with extremely high triglycerides that persist despite standard of care may try to prevent rises in triglyceride levels through dietary restriction of total fat intake, abstinence from alcohol, and avoidance of medications known to increase triglyceride levels.
In a survey of 166 people with FCS, participants reported their restrictive diet was:
81%
extremely time consuming
70%
energy draining
53%
ineffective at stopping all symptoms
Even with treatment, extremely high triglycerides add an emotional and social burden
People with FCS report that their disease impacts their mental well-being and their social lives.
In a survey of 166 people with FCS, the most common emotional symptoms were:
Constant uncertainty about the possibility of acute pancreatitis or pain.
Anxiety, fear, or worry about their health.
Uncertainty about what or how much to eat.
Feeling out of control or helpless because of their FCS.
Percentage of people reporting that FCS has a negative impact on aspects of life:
94%
Employment
58–66%
Emotional and mental well-being
68–82%
Social relationships
An online, anonymous, quantitative survey of people with FCS from 10 countries (Australia, Canada, Germany, India, Netherlands, Portugal, Spain, Sweden, United Kingdom, and United States). Results were patient reported.
Extremely high triglycerides have systemic consequences
In addition to causing acute pancreatitis, FCS can impact the liver, spleen, heart, and eyes, and cause other systemic problems.
Symptoms and comorbidities reported in a survey of 166 people with FCS:
Tap the green hotspot to learn more
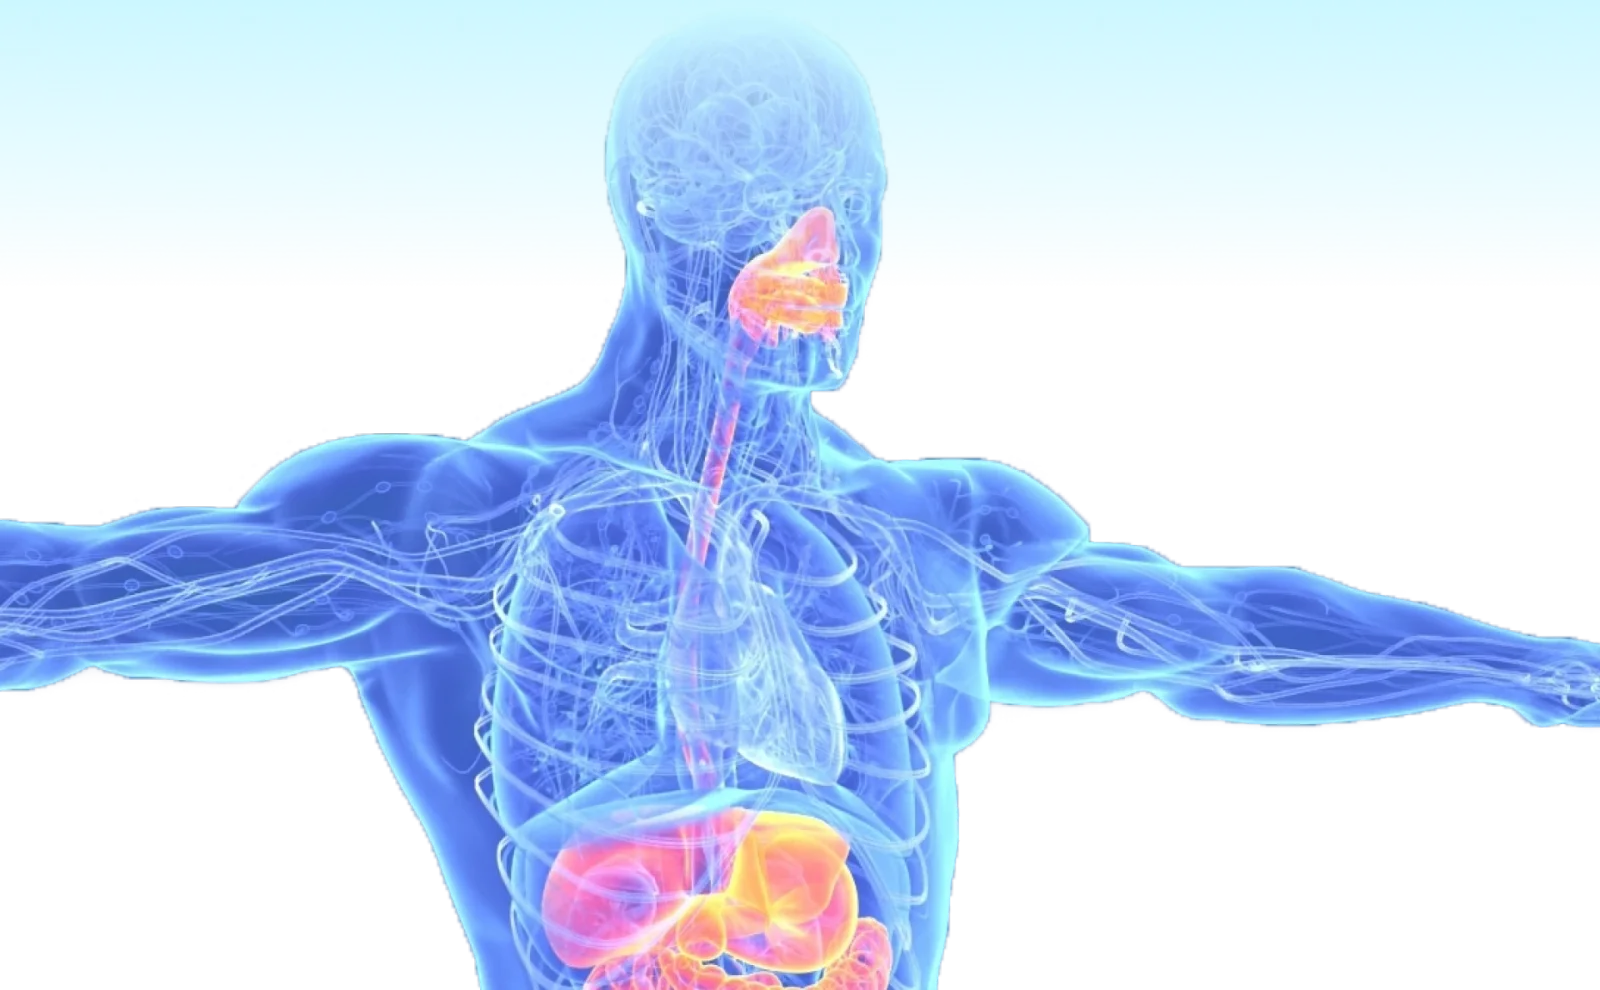
- Difficulty concentrating (16%)
- Impaired judgement (11%)
- Lipaemia retinalis (9%)
- Brain fog (8%)
- Forgetfulness (8%)
- Abdominal pain (41%)
- Acute pancreatitis (40%)
- Bloating (37%)
- Indigestion (27%)
- Diabetes (16%)
- Chronic pancreatitis (11%)
- Enlarged liver (hepatomegaly, 11%)
- Enlarged spleen (splenomegaly, 10%)
- Hypertension (10%)
- Feeling of physical weakness (asthenia, 30%)
- Eating disorders (23%)
- Fatigue (23%)
- Peripheral neuropathy (7%)
Imagine if we could reduce the risk of acute pancreatitis
Expert guidelines support lowering triglycerides below 500 mg/dL to reduce the risk of acute pancreatitis.

Sign up for updates and more information
Receive the latest news and insights about reducing triglycerides to <500 mg/dL.
Show References
- Chait A. Hypertriglyceridemia. Endocrinol Metab Clin North Am. 2022;51(3):539-555.
- Williams L, Rhodes KS, Karmally W, et al. Familial chylomicronemia syndrome: bringing to life dietary recommendations throughout the life span. J Clin Lipidol. 2018;12(4):908-919.
- Shamsudeen I, Hegele RA. Safety and efficacy of therapies for chylomicronemia. Expert Rev Clin Pharmacol. 2022;15(4):395-405.
- Paquette M, Bernard S, Hegele RA, Baass A. Chylomicronemia: differences between familial chylomicronemia syndrome and multifactorial chylomicronemia. Atherosclerosis. 2019;283:137-142.
- Mszar R, Bart S, Sakers A, Soffer D, Karalis DG. Current and emerging therapies for atherosclerotic cardiovascular disease risk reduction in hypertriglyceridemia. J Clin Med. 2023;12(4):1382.
- Handelsman Y, Jellinger PS, Guerin CK, et al. Consensus statement by the American Association of Clinical Endocrinologists and American College of Endocrinology on the management of dyslipidemia and prevention of cardiovascular disease algorithm – 2020 executive summary. Endocr Pract. 2020;26(10):1196-1224.
- Davidson D, Slota C, Vera-Llonch M, Brown TM, Hsieh A, Fehnel S. Development of a novel PRO instrument for use in familial chylomicronemia syndrome. J Patient Rep Outcomes. 2021;5(1):72.
- Gaudet D, Stevenson M, Komari N, et al. The burden of familial chylomicronemia syndrome in Canadian patients. Lipids Health Dis. 2020;19(1):120.
- Davidson M, Stevenson M, Hsieh A, et al. The burden of familial chylomicronemia syndrome: results from the global IN-FOCUS study. J Clin Lipidol. 2018;12(4):898-907.e2.
- Falko JM. Familial chylomicronemia syndrome: a clinical guide for endocrinologists. Endocr Pract. 2018;24(8):756-763.
- Gaudet D, Brisson D, Tremblay K, et al. Targeting APOC3 in the familial chylomicronemia syndrome. N Engl J Med. 2014;371(23):2200-2206.
- Grundy SM, Stone NJ, Bailey AL, et al. 2018 AHA/ACC/AACVPR/AAPA/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA guideline on the management of blood cholesterol: executive summary: a report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines.Circulation. 2019;139(25):e1046-e1081.
- Virani SS, Morris PB, Agarwala A, et al. 2021 ACC expert consensus decision pathway on the management of ASCVD risk reduction in patients with persistent hypertriglyceridemia: a report of the American College of Cardiology Solution Set Oversight Committee. J Am Coll Cardiol. 2021;78(9):960-993.
- Watts GF. Shooting the messenger to treat hypertriglyceridemia. N Engl J Med. 2024;390(19):1818-1823.